
By this point you have likely met the friendly faces of our Transport Team. They travel with their fully functional portable NICU which has everything your baby needs to make it safely to CHEO. Their isolette is heated and your baby is secured in a 5-point harness. Their equipment allows for transport of the most complex NICU patients and our team is specially trained to care for them en route. Members of the team are usually a registered nurse or respiratory therapist who are trained in both roles, called a transport clinician. They are always only a phone call away and in constant communication with the neonatologist (specialized newborn doctor) who approves and recommends the treatments your baby needs. There may not be room in the ambulance or plane for a parent to accompany their baby, but we do our best to accommodate this when possible.
NICU Family Guide
Congratulations on the birth of your baby!
While this is a happy time, we understand that a hospital stay can add a lot of stress and can be a scary time for you and your family. We’re here to help you through it and provide you with what you need to know about your baby’s stay in our Neonatal Intensive Care Unit.
At CHEO we have a level 3 NICU. This means that we provide the highest level of care for babies born at the youngest gestational ages to those at full-term. Your baby is here to receive neonatal intensive care which can include breathing (ventilatory) support and specialty services from one or more of our specialty medical or surgical teams at CHEO.
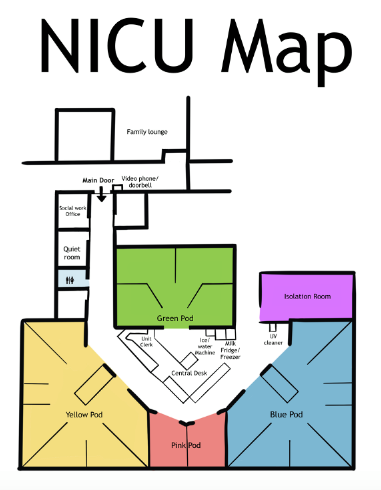
We have three main rooms, which we call “pods” that are identified by colours – yellow, blue and green. There are two rooms near the central desk that make up the “pink pod” The colours do not represent anything other than the location of your baby. Babies of any degree of illness can be in any pod. There are times when we have to move babies from one pod to the other to balance out numbers and keep the workload even for our nurses.
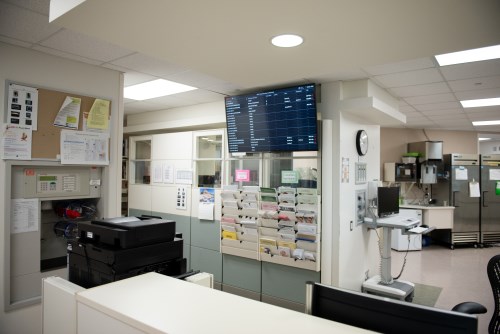
There is a screen located next to the unit clerk’s desk where you can see the location of your baby and the name of the nurse assigned for that shift. If your baby has moved location within the unit, this will always be up to date. Your baby will never be moved outside of the unit without notifying you first.We also have one isolation room. It is used for special procedures and patients with suspected infections.
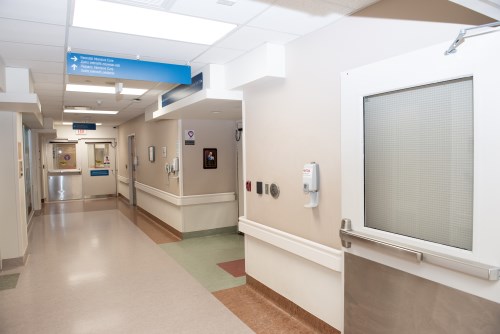
Unit entrance:
NICU clerks desk

Parent, caregiver and visitor presence policies
Please review the following information before arriving at CHEO.
Parents and caregivers are important members of the care team. They actively work with us to provide vital health information only they know and give emotional support in the way only a parent or caregiver can.
For infection prevention and safety reasons, we have limits on how many parents, caregivers and visitors can be onsite at one time. We also limit the number at the bedside.
We appreciate your patience and understanding in keeping everyone safe, particularly during the peak viral season.
Allowed number of parents, caregivers and visitors
Last updated: March 2026
Clinic and Surgical Day Unit appointments
- TWO parents or caregivers are allowed to accompany children and youth while at CHEO for clinic and Surgical Day Unit appointments.
Emergency Department visits
- ONE parent or caregiver is permitted to accompany children and youth while at CHEO's Emergency Department.
Staying at the hospital (admitted to CHEO's inpatient units)
- A maximum of TWO parents or caregivers are permitted at the bedside at a time.
- Only ONE caregiver of immediate family can stay overnight.
Visitors
- During non-peak viral season, visitors are permitted with a maximum of TWO at the bedside.
Exceptions to these rules
We recognize that some families (e.g., people with disabilities) require additional support to help the patients, parents or caregivers. If you are coming to Emergency, please discuss your need for an exception upon arrival at CHEO Emergency. If you are staying as an inpatient, please discuss this with your care team.
Who can't enter
Parents and caregivers who do not pass the entrance screening.
It is important to us that your child or youth receives the care they need. If you require an exception to any of our caregiver/visitor policies to ensure that your child/youth can access care, please contact a member of your care team or reach out to CHEO's Patient Experience team (experience@cheo.on.ca or 613-737-7600 ext. 3078).
Self-screen for illnesses including measles, cold and flu
To make sure we are always putting safety first and minimizing any chance of transmission of infections, please use our quick and confidential illness self-screening tool if you have symptoms or may have been exposed to viral illnesses like cold, COVID, flu or measles.
It will guide you on what to do next and help keep everyone at CHEO safe.
Where to enter
All children, youth, parents/caregivers and visitors must enter through the Main Entrance unless you are seeking care from our Emergency Department. Other entrances are closed.
Frequently asked questions about coming to CHEO
What is the difference between a parent/caregiver and a visitor
Parent/caregiver: Someone who is over 12 years old and helps a child or youth with activities of daily living – e.g., parent, grandparent, older sibling, legal guardian, etc. A parent/caregiver can be designated by a patient. A parent/caregiver is never considered a visitor because they are a vital part of the care team.
Visitor: Someone who is part of a child's or youth’s family or support network (e.g., sibling, extended family member, friend, etc.) but not a designated parent or caregiver.
Will I be required to wear a face mask while at CHEO?
Visit our Infection Prevention and Control at CHEO page for up-to-date information:
For your baby's safety, the NICU is a locked unit. Once you visit the Admitting Office, located near the main entrance, you will be identified as a parent and will receive one unit access pass per family. There is a deposit fee for the pass card which you will be refunded at the end of your stay.
Once you have your access pass, you can swipe yourself in and out of the unit. If you do not yet have an access pass, there is a video phone and doorbell at the NICU doors that you can use for staff to let you in. For everyone’s safety, please do not share your pass with anyone else.

Getting information about your baby
You can call the unit at any time for an update on your baby. When you identify yourself as a parent, ask to talk to your baby’s nurse to receive an update.
There may be times when your baby’s nurse is busy caring for your baby or busy at shift change (around 7:30 both in the morning and in the evening) when they cannot come to the phone. In that case we’ll arrange a call back at a more appropriate time.
Babies in our unit are at high risk for infections and hand washing is one of the best ways to keep them safe.
Start by removing your outside jacket (if applicable) and store it in the shelving unit in the corner of your baby’s room, this is your space.
Next, remove all rings, watches, bracelets and any jewelry below the elbows. Please give a good scrub to your hands, being sure to get beneath the nails, between each finger, and the backs of the hands. Dry thoroughly with the paper towel provided.
Hand washing videos:
You are able to use your cell phone while in the unit. There is a UV cleaner that we recommend you use to sanitize your phone, especially when you first arrive in the unit and before you head into your baby’s room.

It is expected that you use your cell phone for personal use only. You may not take photos or videos of other families or babies without expressed consent.
If you are speaking on the phone, please remember to use a quiet speaking voice or leave the room for your call. As a courtesy to everyone in the room, please use earphones when listening to audio or on a video call. Please keep ringtones and alerts on silent mode.
iPads
If you cannot physically be in the unit due to distance, illness or other circumstances, we can connect with you via teleconference for a brief visit with your baby or to join in daily rounds with the NICU team.
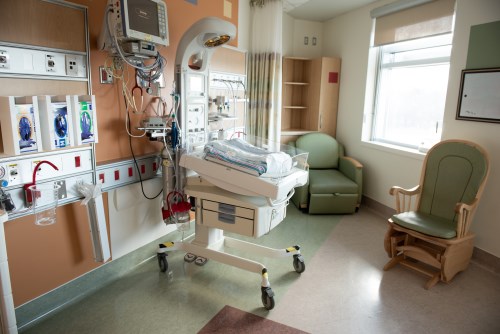
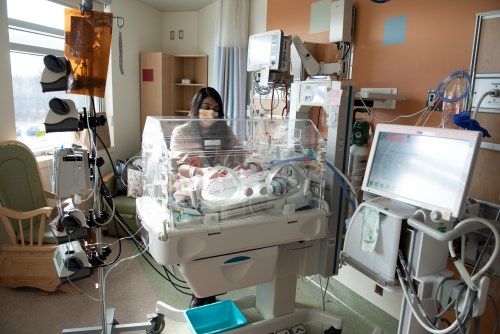
Each room is set up with a bed most appropriate for your baby. This can be a heated overbed, an isolette or a cot. Sometimes there is a lot of equipment setup on all sides of your baby’s bed, depending on their needs. You may use the pull-out bedchair or the rocking chair. The cupboards in the corner are for you to store your jacket, purse and other personal items. Some parents choose to wear indoor shoes while in the unit or bring linens for their baby and store them here.
You’re welcome to bring a photo or a drawing from a sibling to personalize the space. Some choose to bring books to read to their baby and store them here. We can provide a breast milk pump for this corner, and there is a white light switch that is dimmable for you to access an overhead pot light.

In the Ronald MacDonald family lounge across the hall, there is a small kitchenette where you can store meals and heat up with a microwave. Be sure to mark food with your name. There is a second family lounge located on the 5th floor (5 West).
You are welcome to have a small snack or drink from a covered beverage at the bedside, however larger or smell-producing meals are to be kept outside of the unit. You’re welcome to eat your meal in the family lounge, at one of the many picnic tables outside or at the Rainbow Café seating on the 1st floor.
Visit CHEO’s Amenity page for more information.
Staying at CHEO? Order food to your bedside.
CHEO patients, parents and caregivers can now place an online order for food right to the bedside, using the CBORD® Patient™ app! Click here for more information, and to download the app.
There is a pull-out bed chair at each baby’s bedside where one parent can stay the night. The NICU and PICU share a few parent sleep rooms located in the Ronald McDonald Family Lounge. These sleep rooms are reserved for parents arriving from out of town at night or parents whose child is extremely sick or awaiting surgery in the morning and want to remain in hospital. They are intended for short-term accommodation.
Visit CHEO’s Amenities page for information about Ronald McDonald House and Rotel which are located next to the hospital.
Parking is available on-site. To purchase a parking pass, visit the security office, located on the 2nd floor near the emergency department. Many parking pass options are available and our Security team can help you find the most economical option.
The NICU is located on the 3rd level. The main entrance is located on the 2nd level of CHEO. Visit our Maps and Locations page to see maps of each floor at CHEO.

How to get involved in your baby's care
Learn the language of the NICU
Click through our glossary to learn more about the terms and phrases you might hear your baby's care team using. You can click on the letters below to jump to the words starting with each letter.
A B C D E F G H I J K L M N O P R S T U V
A
ABO incompatability
Occurs when the mother has a blood type that does not match with baby’s blood type. It can cause jaundice and anemia in the baby, which will be monitored.
Acidosis
An excess of acid in the blood.
Arterial line
A catheter placed in the artery to monitor blood pressure (invasive) and can be used to draw blood work.
Anemia
Low level of red blood cells or hemoglobin in the body.
Antibiotics
Medicine used to treat bacterial infection
Apgar Score
Scoring tool used at birth that gives a quick idea of how well your baby is doing in the first few minutes of life.
Apnea
A pause in breathing that lasts more than 20 seconds. Common in premature babies.
Aspirate/Aspiration
- When a fluid or air is removed from the baby’s body.
- When baby breathes milk or fluid into their lungs
B
Bilirubin
Yellowish substance made when red blood cells are broken down. Normally processed by the liver and excreted in urine and stool. When it builds up you can notice your baby’s skin or eyes having a yellow/orange colour.
Bili lights
Phototherapy or light treatment that breaks down bilirubin to prevent or treat jaundice.
Breast milk fortifier
Calories and nutrients added to breast milk. May be in powder or liquid form.
Blood gas
Blood sample that tells us how well your baby is exchanging oxygen and carbon dioxide when they breathe.
Birth weight
Measured weight at the time of birth. Sometimes birth weight may be estimated depending on your baby’s condition.
Blood pressure
Can be measured non-invasive lay by using a pressure cuff that inflates or measured invasively by an arterial line in the arms, legs or umbilical cord.
Bolus
An amount of fluid given over a short period of time.
Bradycardia
Slow heart rate. In babies this is noted as under 100 and often worrisome under 60 beats per minute.
C
Catheter
A thin, flexible, plastic tube. There are many types and it may go by different names depending on where it is placed.
Chest X-ray
An X-ray to look at your baby’s chest to see placement of tubes or look at the condition of their lungs or heart.
Chest Tube
Inserted by a physician or advanced practitioner. A chest tube is used to drain fluid or air in the lungs.
CPAP
Continuous positive airway pressure. A machine to help your baby breathe that pushes air through a mask or prongs in their nose to help keep the smallest air sacs in their lungs open and make it easier for them to breathe.
Cyanosis
A blueish colour that is caused by low oxygen saturation. Acrocyanosis is a blueish colour to the hands and feet which can be normal during the first few days of life.
Corrected Gestational Age
The baby’s current age in weeks, starting from the date of conception. For example, a baby born at 35 weeks gestation who is now 5 weeks old would be 40 weeks corrected (term).
D
Desaturation (desat)
When the oxygen level in the blood falls below a set target. This target may vary depending on the baby’s age or condition.
E
EBM
Expressed breast milk. The milk a mother produces.
ECHO
Echocardiogram is an ultrasound of the heart that shows the structure and function of the heart.
Edema
Swelling caused by extra fluid in the tissues of the skin.
Electrolytes
Important chemicals such as sodium and potassium in the blood that must be in balance for the body to work properly.
Exchange Transfusion
Extremely high levels of bilirubin may need to be treated by removing blood from the baby and exchanging it with donor blood to bring down their bilirubin levels.
Extubation
Removing a breathing tube.
F
Fontanelle
There are two soft spots on a baby’s head where skull bones have not yet come together. These are normal and will close within a year.
Full Term
A baby who is born between 37-42 weeks gestation
G
Gastroschisis
A birth defect that allows an opening of the abdominal wall and the baby is born with abdominal organs outside the body.
Gavage feed
Feeding by a tube in the nose (NG) or mouth (OG) which is common when a baby is too premature to eat, or has breathing, digestive or other issues that don’t allow them to take food by bottle or breast.
Gestational Age
The length of time between conception and birth, measured in weeks and days.
GERD
Reflux (or gastroesophageal reflux disease) similar to heartburn, when stomach contents come back up the esophagus. This may cause discomfort or cause premature babies to spell.
GBS
Group B Streptococcus is one of the most common infections babies can be born with and can be quite serious for them. Mothers are routinely swabbed for this around 36 weeks gestation and given antibiotics before the baby is born if possible.
G-Tube
Feeding tube on the abdomen that is surgically placed directly to the stomach. Used for babies who cannot feed by mouth for the long term.
H
Head Ultrasound
Test to check brain structure and blood flow. Routinely monitored in premature babies who are at risk for brain bleeds due to the fragile vessels in their brain.
Heel Prick/Poke/Stick
A way to take blood for testing but using a small lancet on the baby’s heel. Also known as a cap (capillary) sample.
HFO
High frequency oscillation. A type of breathing machine that provides tiny, fast breaths that makes your baby’s chest appear to wiggle. It is a gentle mode of ventilation used when we have difficulty with conventional breaths.
High flow oxygen
Similar to CPAP, a non-invasive breathing support.
Heart Murmur
Additional sound heard in a baby's heartbeat. Sometimes normal in the first day or two of life, but may be an abnormal finding.
Hypoglycemia
Low blood sugar (glucose) level
Hypotension
Low blood pressure
I
Infusion
Intubation
Procedure of placing an endotracheal tube in an airway.
IVH
Intraventricular hemorrhage. A bleed in the brain (into the brain’s usually fluid-filled ventricles) that is common in premature babies. Graded on severity from 1-4.
Isolette
Heated, humidified, double-walled bed for premature babies.
IUGR- Intrauterine growth restriction.
Term used when a baby has slow growth in utero.
J
Jaundice
Yellow colour seen in the skin and eyes common in newborns within the first couple weeks of life. Measured by the bilirubin level which is caused by the breakdown of red cells. If levels are too high, baby may need phototherapy (bili lights) to treat it.
K
Kangaroo Care
Parent holding and undressed baby skin-to-skin on their bare chest.
L
Lipids
Fats delivered by IV which is one part of TPN
Long line
Short of a central line, a long line can deliver IV fluids and medications and remain inserted for up to 30 days.
Level III-B unit
Unit classification that will care for babies of any gestation who require surgical or specialized care.
Lumbar Puncture
Also called a spinal tap. A needle is placed in the lower spine to remove a small amount of spinal fluid for testing. Often used to detect infection in the brain called meningitis.
M
MRI
Magnetic resonance imaging is a test that provides a detailed view of the structures in the body. There are other MR tests that can be performed as well. This is one of the few tests babies must be brought out of the NICU to have done.
Meconium
Dark black or brown, sticky stool babies pass in the first few days.
Meningitis
Infection in the brain that is confirmed with a lumbar puncture to test the cerebrospinal fluid (CSF)
N
NEC
Necrotizing enterocolitis. A condition in the gut of neonates where the wall of the bowel swells and becomes fragile or loses blood flow. It can be very dangerous. The gut may only require some rest and antibiotic treatment before resuming feeds slowly, but in severe cases it may require surgery.
Neonatal
The newborn period of the first 28 days of life.
Newborn Screen
Metabolic screen done on all babies in Ontario. It consists of 5 drops of blood on a paper, usually done by a heel poke. It tests for 5 groups of diseases that are treatable but not usually detected in the newborn period.
NG or feeding tube
Nasogastric tube (NG) is inserted in the nose and travels to the stomach. It can be used for feeding or for draining the contents of the stomach.
Nasal Prongs
Small, flexible tube that delivers oxygen into a baby’s nose.
Nitric Oxide
Gas delivered to open the airways in babies with high pressures in their lungs (pulmonary hypertension)
O
OIT
Oral Immune Therapy involves giving a small drop of freshly expressed breast milk into a baby’s mouth. It allows them to receive antibodies and benefits from the milk before they may be able to feed.
P
PDA
Patent Ductus Arteriosus. A blood vessel that keeps blood away from the lungs when the baby is in utero (when lungs are fluid filled) and usually closes shortly after birth. When it stays open (patent) longer than normal it may interfere with normal blood flow and heart and lung function. We may try medication to close it, or surgery may be necessary.
PHDM
Pasteurized Human Donor Milk. Human breast milk that has been donated to a bank and sterilized to rid it of any possible infection. It still contains many benefits of breast milk and may be easier to digest than formula. It is given to babies who meet certain criteria and may not have their own mother’s milk.
PICC line
Peripherally inserted central catheter looks similar to a regular IV in the arm or leg, but it is a long line that is threaded through the vein to sit at the larger vessels of the heart. It can deliver TPN or medications for as long as needed.
PIV
A peripheral Intravenous is a regular IV. In babies can be inserted into a vein in the hands, feet, arms, legs, or very superficially in the scalp. Babies don’t instinctively protect their IV as adults do. Combined with their fragile veins, the sites don’t always last very long.
Preterm or premature
A baby born before 37 weeks gestation.
Pneumothorax
Medical term for a collapsed lung. It is a pocket of air in the space between the lungs and the chest wall. Larger air leaks may need a needle or chest tube to remove the air as it becomes very difficult to breathe.
Phototherapy
Blue lights that help to lower bilirubin levels and treat jaundice.
PPHN
Persistent pulmonary hypertension of the newborn is high blood pressure in the lungs. This makes it difficult to exchange gasses properly and results in breathing problems.
Pre/post saturations
A measurement of oxygen saturations on the baby’s right hand/wrist and another limb. This gives a quick measure of worsening pulmonary hypertension or a heart condition.
R
Reflux
Similar to acid reflux. Stomach contents backing up into the esophagus. May be painful and may cause small babies to briefly drop their heart rate or stop breathing (spell)
Replogle Tube
Used to keep the airway clear in babies with TEF. It is inserted in the nose or mouth to the back of their throat where their esophagus comes to an end. It has 2 channels in the tube. One continuously infuses saline, while the other continuously suctions away the saline and secretions.
Retractions
Pulling in of muscles that indicates increased work of breathing.
RDS
Respiratory distress syndrome is a breathing problem caused by lack of surfactant in premature babies.
ROP
Retinopathy of prematurity is a disease that affects immature blood vessels in the premature baby’s eye. Babies less than 30 weeks gestation are scheduled for regular eye checkups. In severe cases a laser treatment may be needed.
RSV
Respiratory syncytial virus is similar to a cold, a respiratory infection that can be serious for premature infants and all newborn babies. Some babies will qualify for a vaccine and require this monthly if they are sent home between November-April.
S
Saturation
Percentage of oxygen present and measured in the blood. The red light sensor on your baby’s hand or foot is measuring this.
Skin to skin
See Kangaroo Care under letter K.
Sepsis
A blood infection that requires treatment with antibiotics.
Spell
Apnea and bradycardia in premature babies. Apnea is a pause in breathing of at least 20 seconds that causes their heart rate to drop (bradycardia) and usually accompanied by a drop in their oxygen saturation. It is commonly due to immature breathing centers in the brain and should resolve as they reach term. Sometimes these resolve quickly on their own, but they may require stimulation or intervention to correct.
Stoma
Surgical opening connected to the bladder or bowel that allows waste (urine or feces) to drain out. When connected to the bowel, the name defines which part of the bowel it is connected to, usually colostomy (colon) ileostomy (ileum) or jejunostomy (jejunum). It appears as a small, round, pink piece of flesh attached to the outside of the body. It is covered with a bag to collect the waste.
Sucrose
24% sucrose is a form of sugar in water (less sugar than common syrups such as antibiotics or fever medication) and it’s been proven to reduce pain during tests and treatments in babies up to 18 months.
Suction
Removal of secretions or mucous from lungs, breathing tube, or airway.
Surfactant
Slippery, soapy substance that allows your baby’s lungs to easily open and exchange oxygen. Babies born before 34 weeks may not have produced enough surfactant and may require it to be given via a breathing tube.
T
Tachycardia
Abnormally fast heart beat.
TEF
Tracheoesophageal fistula is a birth defect where there is a small connection between the baby’s windpipe (trachea) and food pipe (esophagus). This will require a surgical correction. See Special Conditions below.
TFI
Total Fluid Intake. This is a set number of milliliters based on your babies age and condition that they need per day. This number is always multiplied by their weight. It is expressed in mLs/kg/day.
Tube (ETT)
Breathing tube. It can be inserted in the nose or mouth to assist a baby with mechanical ventilation. It requires special monitoring and is always at risk of being accidentally removed.
Transfusion
Premature babies may have immature marrow and not produce blood quickly enough. Sometimes oral iron may help boost their stores, but some may require a blood transfusion.
TTN
Transient tachypnea of the newborn is caused by fluid on the lung after birth causing the baby to breathe very quickly. Your baby may need pressure of CPAP and may not be able to feed by mouth while they are breathing so quickly.
Tachypnea
Fast breathing rate
TPN
Total parenteral nutrition is vitamins, proteins, sugars, minerals and fats your baby needs to grow well given by an IV or central line.
U
UAC
Umbilical arterial catheter is a central line placed in the belly button’s artery to monitor blood pressure and may be used for blood sampling.
UVC
Umbilical venous catheter is inserted in the vein in the belly button and is used to deliver fluid, medicine or nutrition to your baby.
V
Ventilator
A machine that helps your baby breathe. Monitored by the Respiratory Therapist.
Every day our NICU Team meets for their daily rounds. Rounds start at 9:30 but it takes a few hours to get around to each patient. The team reviews your baby’s condition over the last 24 hours and makes a plan for the next 24 hours. There is sometimes open discussion or teaching for residents included and a lot of medical terms being said. The team will make sure that you understand all of the important pieces of what was said and give you an opportunity to ask questions. Some parents find it helpful to write down their questions so they don’t forget them when the whole team is there to ask. If a lengthier discussion is needed on a certain topic, sometimes we need to prioritize and come back later to discuss details.
We can arrange to have you attend rounds by secure video conference or fill you in on discussions later in the day if you cannot be there in person.

Because sleep is so important for your baby’s development, we try our best to set a schedule for your baby’s care or “handling” to minimize disruptions. If your baby is being fed, all of their care is then clustered around their feeding times. Often these times are every three hours and either start from 8am or 9am and continue around the clock every 3 hours.
If your baby is not being fed, we may aim to provide care every 4 hours. There may be occasions we will adjust these times to coordinate with a test that needs to be done or based on your baby’s cues.
Sometimes the tubes and wires can be scary and overwhelming. Your baby is still there behind all of it and there are many things you can do to care for them. You can talk or sing to your baby in a quiet voice, but sometimes it is hard to know what to say to your baby. For these times, we are lucky to have books donated to the unit as a special gift from the family of Jack & Mia. You can read this book that is given to your family or any other book you choose to bring in.
You can also hold their hand or show them a small toy. If they are well enough you may be able to try supervised tummy time to help strengthen their back and neck muscles.
You can always get involved in your baby’s care by taking their temperature and washing their face or cleaning their mouth and eyes when needed. You may need some help with the wires at first, but you can help change your baby’s diaper around the time of their feed or handling time.
Family members who cannot visit in-person may want to spend time with the baby by video call. We kindly ask that you use earphones and a quiet voice to respect the space of the other babies in the unit.

When your baby first arrives in the NICU, they usually have several tests or procedures, consults, or exams from physicians which makes daytime quite busy. We also like to give you time to cuddle your baby during the day. This means that we usually reserve bath time for the night shift as there is more available time. Weights tend to be done at the same time as the bath and on Saturday nights we take all of your baby’s weekly measurements (height and head circumference).
As your baby gets better and is moving closer to home, days become less busy with tests and procedures. At this point we encourage parents and caregivers to be more involved in daily care and we can teach you how to bathe your baby during the day or evening if you prefer. While this routine usually works well, let us know early if there is another arrangement that we can try to accommodate.
With your baby’s handling times, you’re welcome to provide care such as eye and mouth care when needed and a diaper change. The nurses will help you navigate all of the equipment and wires.
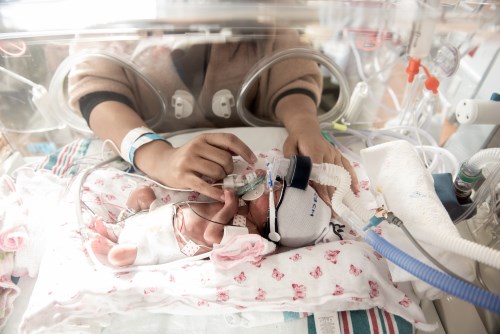
It is common in the NICU that babies are not ready to feed by mouth for the first while for various reasons depending on their condition. In this case, your baby will receive all of the nutrition they need via an IV. This total parenteral nutrition is called TPN and is made up of sugar, electrolytes, vitamins and the fats your baby needs to grow. It is made especially for your baby based on their blood values.
If your baby is ready to receive small amounts of breast milk or formula, this will be offered by a nasogastric tube (NG). The NG tube is inserted in their nose or mouth, travels down their esophagus to their stomach and can deliver milk. If your baby has no issues breathing and is showing signs that they are ready to bottle, breastfeed or chestfeed, they will be allowed to try feeding by mouth. Sometimes it takes a few tries for them to learn how to feed by mouth and build enough energy to get through an entire feed. We often use a feeding tube to give any remaining milk they were unable to take by mouth.
All of our nurses have extensive training and experience helping mothers with breastfeeding or chestfeeding.
From day one we will get you set up with a breast pump and all the information you need to know about pumping. We have pumps available at the bedside and will provide you with one breast pump kit for your stay. It is your responsibility to care for the kit and safely store your milk. If possible, we would like to use fresh milk to feed your baby. Any milk not being used within one hour after pumping needs to be kept cold in the refrigerator or on ice and labeled with the date and time you pumped. Our pumps cannot be removed from the hospital. If you choose to go home overnight and need to pump, you may need to purchase or rent a pump for home. We can instruct you where to find a rental pump. In the meantime, you can always use hand expression to help keep your supply up and for comfort.
Expressed breast milk (EBM) can be stored:
- in the fridge for up to 48 hours
- in the freezer up to 3 months
- in a deep freezer up to 6 months
Once thawed out, it is good for 24 hours.
As much as possible, we encourage all parents to provide kangaroo care which involves uninterrupted time for either parent to hold your baby skin to skin. Your baby will be in just a diaper and rest on your bare chest.
We recommend that you make sure you’ve had something to eat and drink and gone to the bathroom prior to holding your baby. This will help make sure you are available for at least 60 minutes but kangaroo care can last several hours if you’re able. It can take some time after transferring to your skin before your baby really settles in and it is best to minimize disruption. This time is so precious with your baby and we advise you to soak it all in and not pick up your phone and maintain skin to skin contact with your baby for as long as possible.
Benefit of Kangaroo Care for babies
Skin-to-skin or kangaroo care has been shown to have many benefits for your baby. It helps them:
- Regulate their breathing, heart rate and temperature
- Prepare them for breastfeeding or chestfeeding
- Manage pain during painful procedures
- Decrease crying and stress
Studies show when you and your baby are skin to skin in the same environment, you produce antibodies to microorganisms in this environment which. These antibodies appear in your breast milk within a few hours and the immunity is passed on to your baby. It also is shown to help with sleep and brain development
Benefits of Kangaroo Care for parents:
- decreases parental stress
- helps you gain confidence in caring for your baby
- is an opportunity to bond with your baby
- improves milk production and eases the transition to breastfeeding or chestfeeding
- decreases risk of postpartum depression
Modified Kangaroo Care
If your baby’s condition prevents them from being held, there are modified forms of kangaroo care you can provide.
Finger Holding – your baby can hold your finger as a comfort measure
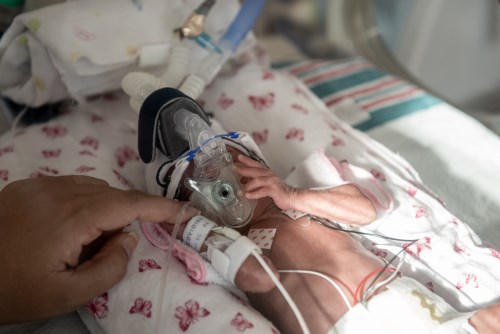
Hand hugging – place one hand around your baby’s head and the other cupping their feet to help calm them and feel secure.
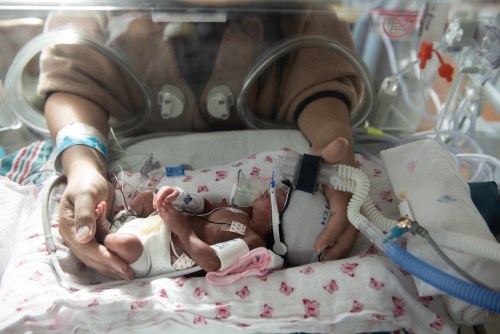
Nesting or encircling baby – you can lean over their bed and wrap your arms around your baby

More information
You may choose to bring in some blankets, facecloths, or clothes for your baby. Make sure items are washed in a scent-free detergent prior to bringing them in. Your home should be smoke-free before your baby’s arrival as the scent of smoke can cause them difficulty breathing. Make sure your items are labeled with their name (usually on a tag). While we try our best to keep things clean, babies are messy beings. Blankets will frequently be soiled and have to be brought home to be laundered. Just in case, do not bring items that are very precious to you or you would not like to be lost or accidentally damaged.
Your journey in the NICU with your baby is unique. Thanks to the CHEO Foundation, we have created a bravery beads program. In the parent area of the NICU you will find colourful beads that each have a special meaning. You can create a representation of your baby’s journey in the NICU by collecting a special bead for each test, procedure or occasion they go through. Each one has a meaning and this collection you create will be a testament to their story for years to come.
As your baby’s health improves, they may not need NICU care any longer. If they are not requiring the specialty care of our NICU, there are times when it is appropriate to send them back to their birth hospital or transition to another unit at CHEO before they’re ready for home. While the care may look different in different areas, know that this is a positive move towards the goal of you bringing your baby home. This will give you the opportunity to become even more involved in your baby’s everyday care.
What you can do to ease this transition?
Get involved in your baby’s care early on. While you are in the NICU, try to learn as much as you can to become the expert in your baby’s care. If your next step is the inpatient wards at CHEO, parents are expected to stay with their baby. Most parents who have had their baby home already want to stay and are used to caring for their child. This parent-led care model can be a big change for parents of babies who have been in the NICU but this is progress towards going home! Learning how to lead your baby’s care early on will help.
Ask for help! Child Life is there to improve your child’s experience. They can help coordinate volunteers to cuddle your baby when you need a break. Social Workers are there to support you and help you navigate the health care system. Spiritual Support are there to listen and help you through difficult times. Patient Experience is there to respond to questions or concerns you may have about your time at the hospital.
Feeding in the NICU
Most babies who need to come to the NICU may not be able to feed as they normally would for the first few days or longer. For various reasons, both term and premature babies may have issues with breathing or digestion that prevent them from feeding. Initially, they will receive all of the sugars and electrolytes they need by intravenous (IV) fluids.
If you plan to breastfeed, chestfeed, or provide your baby with expressed breast milk, you should start expressing milk as soon as possible. In the first few days your milk is darker and thicker, called colostrum. Save every drop! We call it Liquid Gold and it contains many protective factors to line your baby’s digestive tract. Even if your baby isn’t ready to feed, we can put a small drop in their mouth which we call Oral Immune Therapy (OIT). It helps get your baby’s bowel started on the right track.
If it is determined that your baby cannot eat for more than a few days, we will add in extra nutrition that includes all of the vitamins, proteins and fats they need to grow and thrive. This intravenous (IV) nutrition is called Total Parenteral Nutrition or TPN. Your baby’s TPN is prepared every day and adjusted to your baby’s specific nutrition needs based on their blood values. They will have regular blood work drawn to make sure they’re getting the right amount of everything they need. We will often make adjustments in the rate of TPN as we try giving your baby more of your milk by mouth or through a feeding tube.
When a baby is ready to start receiving milk, there may be several reasons why we need to start with a tube or bottle feed. Premature babies start to develop a stronger suck and coordinate with their swallow around 32-34 weeks gestational age. Some full term babies may not be able to feed by mouth if they have breathing, neurological, digestive or other issues. If your baby’s breathing or suck prevents them from being able to take their feed by mouth, we will insert a nasogastric (NG) tube in their nose that will deliver the food directly to their stomach. This allows your baby to safely receive milk without the risk of choking (aspiration). Tube feeding allows them to save their energy for growth and development.
After not feeding for some time, your baby will start with a small amount of breast milk or formula. This small amount of milk that is meant to get your baby’s digestive tract used to the idea of feeding is called a trophic feed. When your baby is tolerating trophic feeds we will slowly increase the amount of milk they receive.
Breastfeeding or chestfeeding in the NICU
Your human milk is designed to give your baby everything they need. Mothers of premature babies produce milk with a different makeup than those of full term babies. It has more calories and a different nutritional makeup that changes as your baby grows. When your baby is old enough and healthy to feed on their own, they will begin showing signs of readiness to feed. Opening their mouth, rooting and showing a strong suck are all some of the signs they’re ready to start feeding. Even for full-term, healthy babies this sometimes takes a bit of practice, patience and learning for both mother and baby. Your baby’s nurse can share tips to help you succeed.
For more information on breastfeeding or chestfeeding, please visit our CHEO breastfeeding and chestfeeding resource page
Breastfeeding or chestfeeding in the NICU
For parents who are choosing to breastfeed, expressed milk is the best gift you can give your baby until they are ready to go to the breast. It contains so many nutrients and protective properties for their bowel and immune system. It’s no secret that expressing your milk is a lot of work. Even if only for the first few feeds, mother’s milk is proven to provide your baby with lifelong benefits.
We have a double pump for you to use, available at your baby’s bedside. We provide you with one kit that you will be responsible for caring for throughout your stay in the NICU. There is also a lactation room in the Ronald McDonald Family Lounge where you can find a dishwasher to sterilize your kit once a day. In between you will be provided with a bowl and dish soap to wash and air dry your kit at the bedside.
After delivery, the hormone prolactin which helps you produce milk increases. You need to stimulate the breast tissue to encourage milk production. Early breast massage or hand expressing is the best and easiest way to remove this early milk called colostrum. We encourage you to express your milk every 2-3 hours. It may be helpful to set an alarm to keep you on track. During the first few days or weeks it will be necessary to pump through the night as prolactin levels are highest between 02:00-04:00 in the morning. You can find more information on pumping and milk production here.
We recognize that it is a balancing act between sleep, nutrition, your pumping schedule and all of your demands. While you may have never considered pumping when you envisioned taking care of your newborn, keep in mind it is hopefully one step towards breastfeeding or chestfeeding your baby one day soon.
A Pumping log that may be helpful for you to track the times and amount you pump each session. You may be able to notice trends such as whether your supply increases or decreases based on stress, nutrition, when you spend time near your baby or frequency of pumping.
There are many advantages to expressing milk by hand and it may even be the best way to express colostrum during the early days. Colostrum is particularly thick, rich and nutritious for your baby, but the thick milk can be difficult to extract using an electric pump. Hand expression really helps you get deep into the tissues to help stimulate production and clear the ducts.
Here is a short video from BC Women's Hospital that explains the technique.
To know when your baby is ready to feed, we will look for cues they are ready to feed. When the medical team has cleared your baby to feed, we will look for signs they are ready to feed such as sucking, rooting or opening their mouth, licking, or bringing their hands to their mouth. If your baby is sleepy, there are some ways of gently waking them. It might be necessary to try timing feeds with moments when they are already awake and keen to feed. With time, they will feel more hungry and be keen to feed.
If your baby is not feeding by mouth yet, it is important to create positive oral experiences for them. Providing opportunities for non-nutritive sucking such as a pacifier or soother, allowing them to nuzzle at the breast, or sucking on a clean, upside down finger in their mouth to soothe all help create a positive oral experience for your baby. You can also gently stroke their cheek and speak to them when they are happy. Providing a drop of breast milk on their tongue, called Oral Immune Therapy and may be a positive oral experience that also allows them to smell and taste your breast milk while also providing them with antibodies from your milk.
Whichever type of nutrition your baby is receiving, their growth will be closely monitored. We measure their weight daily if possible. The doctors, dietician and nurses will make adjustments to their feed if needed. Premature babies or those with a cardiac condition may require extra calories or nutrients added to their milk.
Sometimes babies require additional nutrition to grow and thrive. There are two types of fortifiers that could be added to your breastmilk; one is made from cow’s milk and the other is made from human milk. Be sure to speak to your baby’s neonatologist and dietitian to understand all of the options and what is best for your baby. You can find more information on breastmilk fortifiers from PreemieWorld here.
Some babies who are born very premature or with certain gastrointestinal (GI) issues may qualify to receive Pasteurized human donor milk (PHDM).
There are strict criteria for those who qualify to donate and all milk is collected under strict conditions and stored in a human milk bank. It is then pasteurized to remove any potential germs, yet still contains all of the benefits of breastmilk. This is a similar process that happens with cow’s milk that you buy in the grocery store.
We do not allow for milk sharing or wet nursing in the NICU.
If you have excess milk supply and are interested in donating breastmilk for premature and critically ill infants in our province, you can find out more information on Milk Bank Ontario's website.
Neonatal Encephalopathy (HIE and cooling)
Please see the selection of helpful information that may be relevant to your stay in NICU or useful for when you’re at home with your baby,
What is Neonatal Encephalopathy (HIE and cooling)?
It is a general term that means swelling or injury in the newborn brain that disturbs its function. There are many ways this can happen before, during or shortly after a baby is born. Hypoxic Ischemic Encephalopathy (HIE) is the most common type we see. It is caused by a lack of oxygen at birth can be caused by problems with blood flow from the placenta to the baby. Other causes are neonatal stroke- which is a bleed in an area of the brain- or it can be caused by problems with the baby’s breathing after birth, sometimes due to metabolic issues or an infection in the amniotic fluid.
Some babies with this kind of issue at birth may benefit from therapeutic hypothermia. This is a cooling treatment that lowers the baby’s whole body temperature by a few degrees to slow down brain activity and slow the swelling response. The cooling helps to limit further injury to the brain and helps with recovery.

To help understand how cooling can help, think of how and why a bear hibernates in the winter. When winter comes, a bear’s food is in short supply. Their body temperature lowers and their breathing and heart rate slow down. By reducing the energy demands on their body, they’re able to go many months without food. As in any injury, after a traumatic birth, the body’s natural reaction is inflammatory to help heal, which causes swelling. By cooling your baby, this limits the amount of swelling, similar to how you could ice an injury. When a baby is cooled, their body’s demands are slowed, in particular in the brain, which helps prevent further injury.
If you’ve heard the expression “don’t poke the bear” that is because they require a lot of energy to suddenly increase their heart rate, breathing rate and temperature. While babies who are cooling will often wake on their own, it is very important to respect their sleep cycles and allow their developing brain time to heal.
- Hypothermia- For 72 hours your baby’s temperature will be about 3 degrees cooler than normal at 33.5 degrees Celsius
- Integrated family care -We encourage you to be as involved in your baby’s care as possible. Talk to your baby’s nurse about the many ways to be involved. You may be able to have a cool cuddle but sometimes modified holding is best.
- Boundaries – used to keep baby well aligned. Your baby’s positioning is important, especially if they are very sick or sedated.
- Environment. We will create a neuroprotective environment to promote brain healing.
- Rest and recovery. Recognize your baby’s sleep-wake cycles and avoid disruption. Help them recover after handling
- Nutrition. We will start to feed small amounts of milk to prime their gastrointestinal tract as early as possible. The rest of their nutrition will be given by their IV since their gut may have injury as well and may move more slowly while they are cooling.
- Assessment- your baby will need regular, targeted neurological assessments as well as their routine head to toe assessments by their nurse and medical team.
- Tools- we have specialized assessments for your baby’s pain and skin condition during this time
- EEG- There is a high risk for seizures during this time. An EEG is a brain monitor that can detect seizures.
While there are many necessary tests and interventions at this time, it is important to maintain a quiet, calm environment for your baby. There are ways to get involved in your baby’s care. We encourage you to ask your baby’s nurse how you can best provide comfort when they are awake. While it might feel like forever, hibernation only lasts three days and is an important period of healing.
The following websites explains much of what you can expect during your NICU stay when your baby is cooling and also what you can expect after as they grow and recover:
Have you registered for MyChart?
MyChart is a free, secure, online patient portal that connects patients to parts of their CHEO electronic health record, anywhere, at any time.